












Abdominal Compartment Syndrome
Also known as: ACS
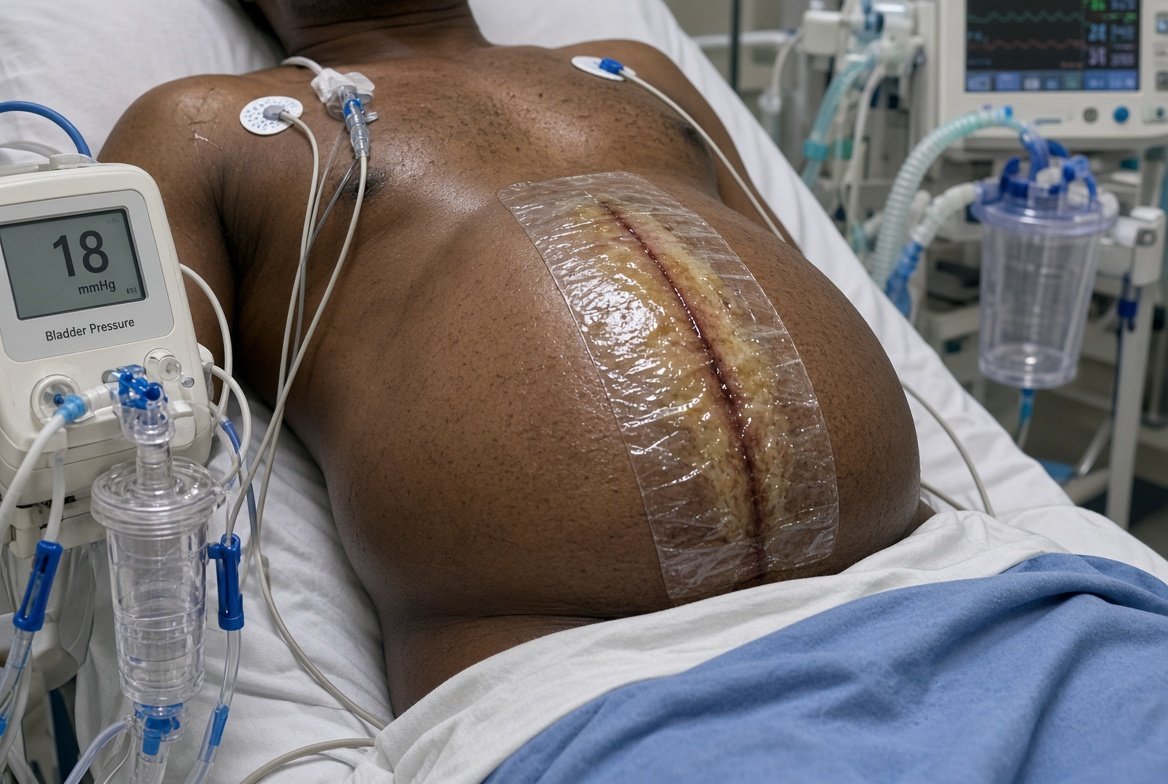
Abdominal compartment syndrome (ACS) is defined as sustained intra abdominal pressure (IAP) above 20 mmHg, with or without an abdominal perfusion pressure below 60 mmHg, that is associated with new organ dysfunction or failure. Intra abdominal hypertension (IAH) is sustained or repeated IAP of 12 mmHg or above. Normal IAP in a critically ill adult is about 5 to 7 mmHg.
IAH is graded: grade I, 12 to 15 mmHg; grade II, 16 to 20 mmHg; grade III, 21 to 25 mmHg; grade IV, above 25 mmHg. Abdominal perfusion pressure (APP) equals mean arterial pressure minus IAP, and a target of at least 60 mmHg is associated with better survival.
Classification:
- Primary ACS arises from injury or disease within the abdominopelvic region (trauma, ruptured aneurysm, pancreatitis, bowel obstruction, perihepatic packing, retroperitoneal haemorrhage, liver transplantation)
- Secondary ACS arises from conditions outside the abdomen (massive fluid resuscitation, sepsis, burns, capillary leak)
- Recurrent ACS develops again after prior surgical or medical treatment
Pathophysiology is a vicious cycle. Raised IAP reduces venous return and cardiac preload, compresses the inferior vena cava, raises systemic vascular resistance, and elevates the diaphragm, which lowers lung compliance and raises airway pressures.
Renal perfusion falls through direct renal vein and parenchymal compression, causing oliguria. Splanchnic perfusion falls, producing bowel ischaemia, bacterial translocation and visceral oedema, which in turn raises IAP further.
Intracranial pressure rises through increased intrathoracic and jugular venous pressure.
Risk factors include large volume crystalloid resuscitation (above 5 L in 24 hours), massive transfusion, acidosis (pH below 7.2), hypothermia (below 33 degrees C), coagulopathy, sepsis, ileus, mechanical ventilation with high PEEP, obesity, and abdominal packing or tight closure.
