












Abdominal Wall Dehiscence
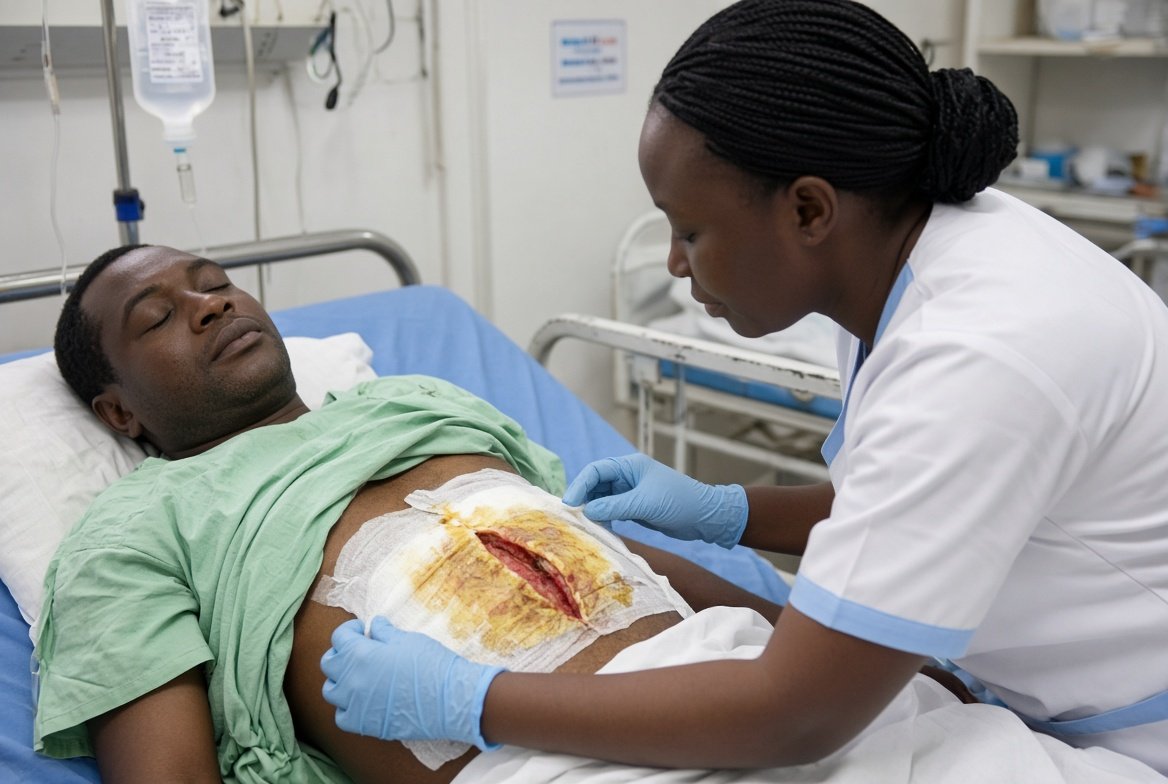
Abdominal wall dehiscence (fascial dehiscence, burst abdomen) is the partial or complete separation of the fascial layer of a laparotomy closure, allowing abdominal contents to push through the wound.
Evisceration is the extrusion of bowel or omentum through the skin as well. Incidence after midline laparotomy is 1 to 3% (up to 10 to 15% in high risk emergency surgery).
Mortality in complete dehiscence with evisceration is 10 to 45%, mostly from the underlying disease and sepsis.
It most often becomes apparent between day 5 and day 10 after surgery, but may occur earlier or later.
Failure of the fascial closure is a mechanical problem with a biological contribution: sutures cut through fascia that has lost strength because of infection, ischaemia, malnutrition or poor healing, while raised intra abdominal pressure pulls the closure apart.
Risk factors:
Patient: age above 65, male sex, obesity, malnutrition (low albumin below 30 g/L), anaemia, diabetes, smoking, chronic cough or COPD, steroid or immunosuppressive use, chemotherapy or bevacizumab, uraemia, jaundice, malignancy, connective tissue disease, previous laparotomy
Operative: emergency surgery, contamination, long operation time, midline incision, poor suture technique (large tissue bites, too tight, too few), suture material too fine or short lived, wound infection, intraoperative hypotension
Postoperative: ileus and distension, abdominal compartment syndrome, coughing, vomiting, straining, early heavy lifting, SSI, haematoma, seroma
Prevention is central.
Evidence based closure technique is the small bites technique: a continuous monofilament slowly absorbable suture (for example PDS 2-0 or looped PDS 1) placed 5 mm from the fascial edge and 5 mm apart, with a suture-to-wound length ratio of at least 4:1, closing with no undue tension.
Prophylactic onlay or retrorectus mesh reinforcement in high risk patients reduces incisional hernia and may reduce dehiscence.
