












Iron Poisoning
Also known as: Iron overdose
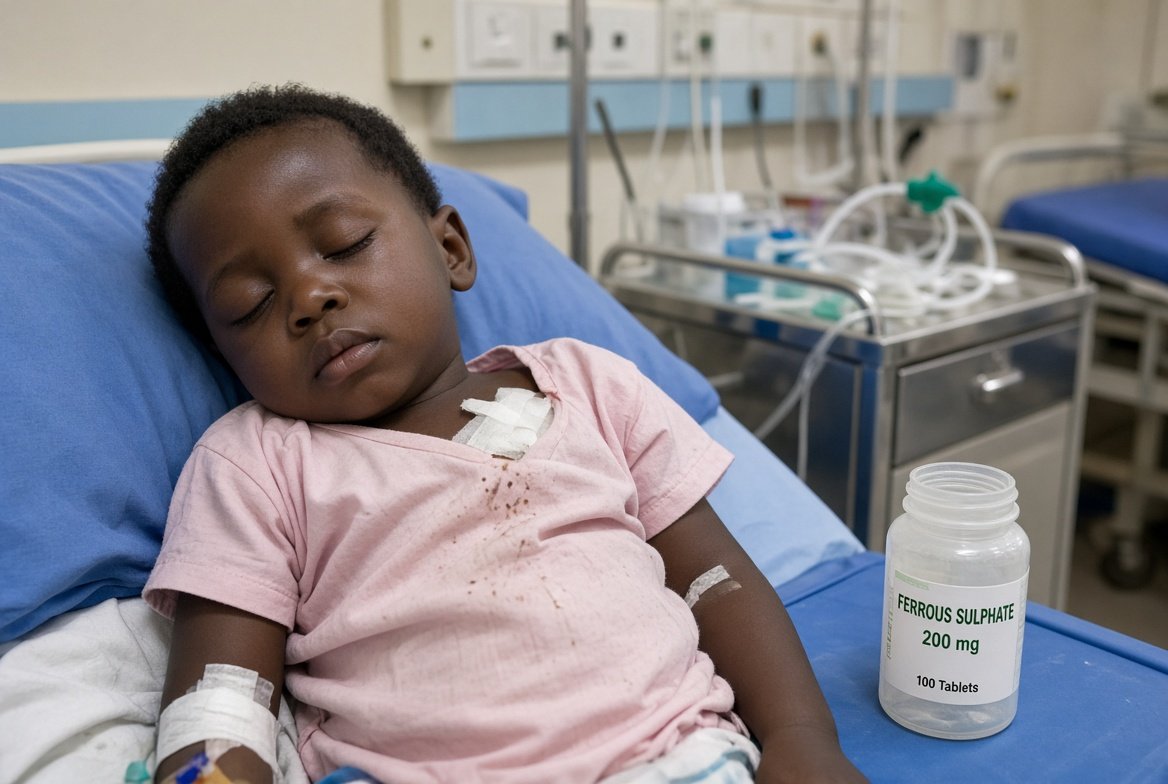
Iron poisoning is most commonly seen in young children who have accidentally ingested iron containing tablets, often a caregiver's prenatal or therapeutic iron supplement, though it also occurs in deliberate adult overdose.
Toxicity results from direct corrosive injury to the gastrointestinal mucosa at the site of ingestion, and, once absorbed in excess of the body's binding capacity (transferrin and ferritin), from free iron causing cellular toxicity, particularly within mitochondria, across multiple organ systems, notably the liver.
Classically described in stages, though the boundaries between them can be less distinct in practice:
- Stage 1 (0 to 6 hours): gastrointestinal symptoms from direct corrosive injury, nausea, vomiting (sometimes hematemesis), abdominal pain, and diarrhea. Significant toxicity may be absent at this stage even with a substantial ingestion, so an asymptomatic early presentation does not exclude a dangerous ingestion.
- Stage 2 (6 to 24 hours): a deceptive, apparent recovery phase, during which the patient may appear clinically improved while systemic iron toxicity is, in fact, evolving. This stage is a recognized trap for underestimating severity.
- Stage 3 (12 to 48 hours): systemic toxicity becomes apparent, with metabolic acidosis, hypotension and shock, coagulopathy, and, in severe cases, hepatic failure and multi-organ dysfunction.
- Stage 4 (2 to 6 weeks): gastrointestinal scarring and stricture formation, particularly at the pylorus, from the initial corrosive mucosal injury, presenting later with obstructive symptoms.
- A serum iron level, ideally taken 4 to 6 hours post ingestion (the typical peak), guides severity assessment and management, interpreted alongside total iron binding capacity where available.
- An abdominal X-ray can be useful, since iron tablets are radiopaque and may be visible in the gastrointestinal tract, helping confirm ingestion and estimate the residual tablet burden, though a negative X-ray does not exclude significant ingestion if tablets have already dissolved or if a liquid or chewable formulation was involved.
- Venous blood gas and lactate assess for metabolic acidosis, an important marker of systemic toxicity.
- LFTs and coagulation profile should be checked, given the risk of hepatotoxicity in significant poisoning.
- FBC and glucose are checked as part of general assessment; a normal white cell count and glucose have historically been suggested as reassuring, though should not be relied upon in isolation given limited predictive value.
Differentials include other causes of gastrointestinal upset and, in more severe presentations, other causes of an anion gap metabolic acidosis with shock.
Assessment of ingested dose, calculated as elemental iron per kilogram body weight, guides initial risk stratification, recognizing that formulations vary considerably in their elemental iron content.
- Whole bowel irrigation with polyethylene glycol solution is considered for significant ingestions, particularly where tablets are visible on abdominal X-ray, to reduce ongoing gastrointestinal absorption; activated charcoal is not effective for iron and should not be used for this specific purpose.
- Aggressive intravenous fluid resuscitation addresses hypovolemia and shock where present.
- Desferrioxamine, an iron chelator, is the specific antidote for significant systemic toxicity, given as an intravenous infusion, binding free iron to form a water soluble complex (ferrioxamine) that is renally excreted; it is generally reserved for patients with significant systemic symptoms, shock, significant metabolic acidosis, or high serum iron levels, rather than given routinely for all ingestions.
- A classic, though not entirely reliable, clinical sign of chelation is a pink or vin rosé discoloration of the urine as ferrioxamine is excreted.
- Ongoing supportive care addresses evolving complications, including correction of acidosis, management of coagulopathy, and monitoring for hepatic injury.
Referral: poison control or toxicology service for all significant ingestions; pediatric emergency or general emergency medicine input for risk stratification and decision on whether chelation and admission are warranted.
