












Postpartum Haemorrhage
Also known as: PPH, Postpartum hemorrhage
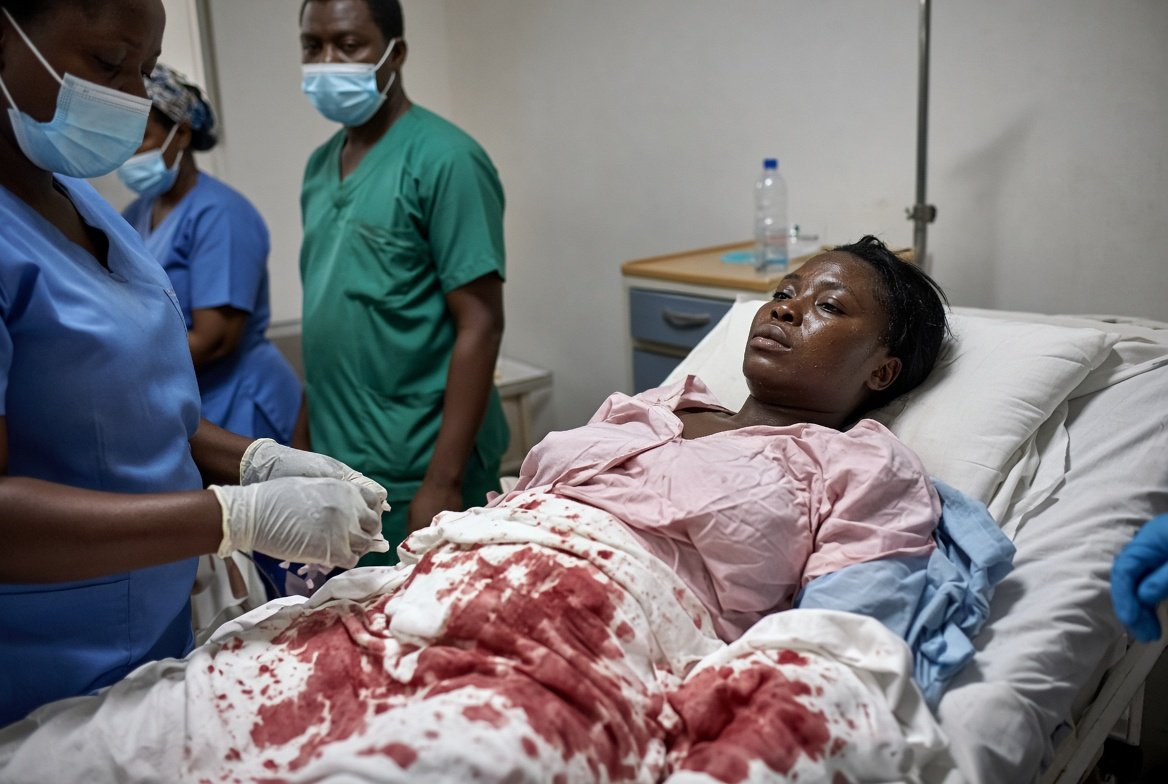
Postpartum haemorrhage is excessive bleeding after childbirth. It is conventionally defined as blood loss exceeding 500 mL after vaginal delivery or 1000 mL after caesarean delivery.
It is a leading cause of maternal mortality worldwide and a significant cause of severe maternal morbidity even in well-resourced healthcare settings.
It is classified as primary or secondary. Primary haemorrhage occurs within the first twenty-four hours after delivery and accounts for the substantial majority of cases. Secondary haemorrhage occurs from twenty-four hours up to six weeks postpartum.
The causes are conventionally organised by the "four Ts" framework (tone, trauma, tissue, and thrombin). It gives a structured, systematic approach to diagnosis and management of this time-critical obstetric emergency.
Classification and pathophysiology
- Uterine atony (failure of adequate uterine contraction after delivery, "tone") is by a substantial margin the commonest cause of primary postpartum haemorrhage.
- Coordinated, sustained uterine contraction compresses the spiral arteries at the placental implantation site and achieves haemostasis.
- Risk factors for atony include uterine overdistension (multiple pregnancy, polyhydramnios, or macrosomia), prolonged labour, chorioamnionitis, and a history of previous postpartum haemorrhage.
- Genital tract trauma ("trauma") is a further important cause. It includes perineal, vaginal, cervical, or, less commonly, uterine trauma (including uterine rupture). It is particularly relevant after operative vaginal delivery, precipitate delivery, or a large infant.
- Retained placental tissue or membranes ("tissue") prevent adequate, sustained uterine contraction at the site of retention.
- The placenta accreta spectrum is a particularly high-risk cause of major haemorrhage and an important structural cause.
- Coagulopathy ("thrombin") is a further important, though less common, underlying or contributing cause. It may be pre-existing, such as a known inherited or acquired bleeding disorder.
- It may also be acquired during pregnancy or delivery, including disseminated intravascular coagulation secondary to placental abruption, amniotic fluid embolism, or severe pre-eclampsia.
- Secondary postpartum haemorrhage most commonly reflects retained products of conception or endometritis. It presents somewhat after the more immediately apparent primary haemorrhage causes.
