












Vaginal Candidiasis
Also known as: Thrush
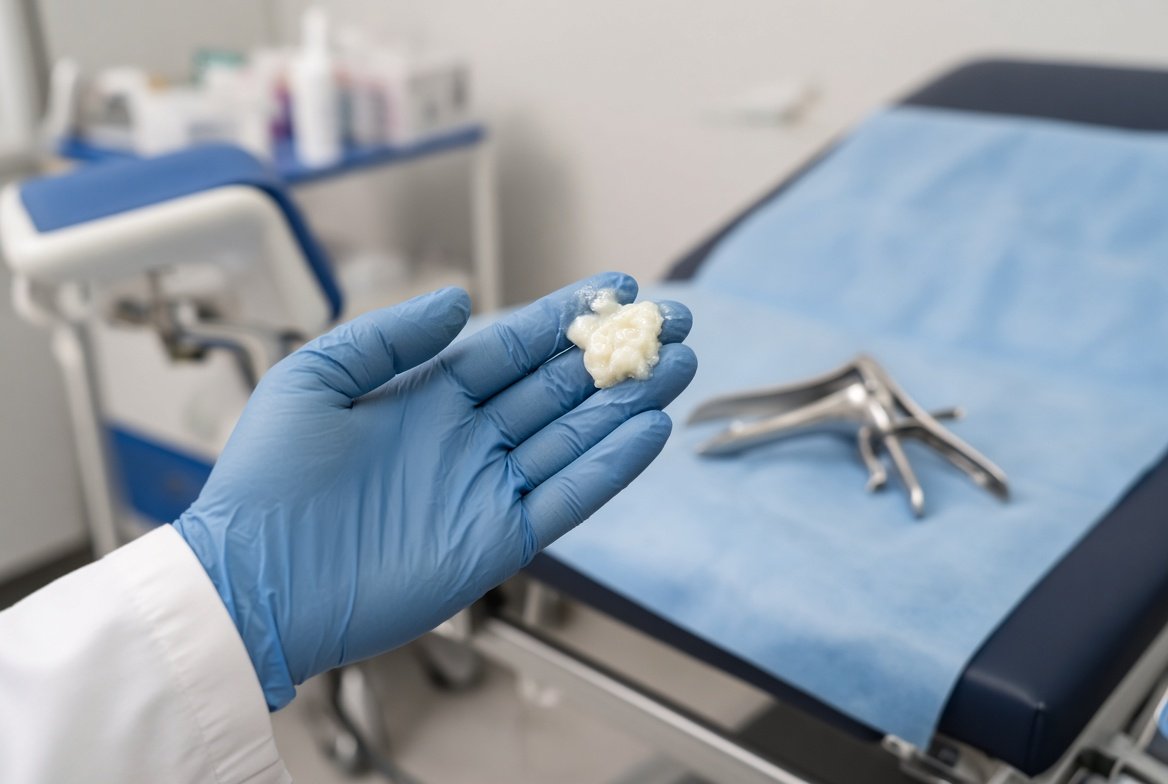
Vulvovaginal candidiasis is symptomatic inflammation of the vulva and vagina caused by Candida. It affects about 70 to 75 percent of women at least once and recurs in about 5 to 8 percent. Asymptomatic vaginal colonisation (10 to 20 percent of women of reproductive age) is not treated.
Candida albicans causes 85 to 90 percent of cases. Candida glabrata is the commonest non albicans species and is more frequent in older women, in diabetes and after repeated azole use. Other causes are Candida parapsilosis, Candida tropicalis and Candida krusei.
Disease is rare before menarche and is uncommon after menopause unless hormone therapy, diabetes or immunosuppression is present.
Vaginal candidiasis is driven largely by the host inflammatory response to hyphal Candida, and by loss of colonisation resistance. Candidalysin and secreted aspartyl proteases activate the NLRP3 inflammasome and recruit neutrophils, whose accumulation causes symptoms without clearing the fungus. The normal vaginal pH of 4.0 to 4.5 is maintained.
| Risk factor | Mechanism |
|---|---|
| Recent antibacterials | Loss of lactobacilli |
| High oestrogen (pregnancy, high dose oral contraceptives, hormone therapy) | Increased glycogen and fungal adherence |
| Diabetes, particularly poorly controlled | Glycosuria and impaired neutrophil function |
| SGLT2 inhibitors | Genital glycosuria |
| Immunosuppression, corticosteroids, HIV | Reduced local and systemic defence |
| Intrauterine device, diaphragm, spermicides | Biofilm and altered flora |
| Tight, occlusive or synthetic clothing, moisture | Local environment |
| Genetic susceptibility | Mannose binding lectin and Dectin 1 variants, and a blood group effect in some series |
| Oral sex, sexual activity | Increased frequency, but not classified as a sexually transmitted infection |
- Vulvar pruritus, the most consistent symptom, with burning, soreness, dyspareunia and external dysuria.
- Vulvar erythema, oedema, fissures and excoriation, sometimes with pustulopapular satellite lesions.
- Vaginal discharge that is thick, white and curdy (cottage cheese like), or thin and watery, or absent. It is odourless.
- Cervix is normal. Vaginal pH is normal, at 4.5 or lower.
| Category | Definition |
|---|---|
| Uncomplicated | Sporadic or infrequent, mild to moderate, probably Candida albicans, in an immunocompetent woman |
| Complicated | Recurrent (three or more symptomatic episodes in 12 months), severe (extensive erythema, oedema, excoriation, fissures), non albicans species, or an abnormal host (poorly controlled diabetes, immunosuppression, pregnancy) |
Male partners may develop balanitis or balanoposthitis, with erythema, pruritus, small pustules and a white coating beneath the foreskin. It is treated topically, and diabetes is excluded.
| Condition | Discriminating features |
|---|---|
| Bacterial vaginosis | Grey, fishy discharge, pH above 4.5, clue cells, positive whiff test; pruritus uncommon |
| Trichomoniasis | Frothy yellow green discharge, pH above 4.5, motile trichomonads, strawberry cervix; sexually transmitted |
| Contact and irritant dermatitis (soaps, wipes, spermicides, latex) | Burning and erythema with no discharge, no yeast |
| Atrophic vaginitis | Postmenopausal; dryness, dyspareunia, high pH |
| Lichen sclerosus, lichen planus, eczema, psoriasis | Skin changes of the vulva; biopsy |
| Cytolytic vaginosis | Excess lactobacilli, low pH, cyclic symptoms, no yeast |
| Herpes simplex | Painful ulcers or vesicles |
| Desquamative inflammatory vaginitis | Purulent discharge, parabasal cells, high pH |
| Vulvodynia | Chronic pain with a normal examination and negative tests |
| Aerobic vaginitis | Purulent discharge with abnormal flora |
- Vaginal pH: 4.5 or lower in candidiasis. A raised pH points to bacterial vaginosis, trichomoniasis or both.
- Wet mount in saline and 10 percent potassium hydroxide: budding yeasts, pseudohyphae or hyphae. Sensitivity is about 50 to 70 percent, so a negative result does not exclude infection in a symptomatic woman.
- Gram stain: yeast and pseudohyphae, and a lactobacillus dominant flora.
- Culture: indicated for recurrent or refractory disease, when microscopy is negative in a symptomatic woman, and for species identification. Isolation of Candida without symptoms is colonisation.
- Species identification and susceptibility testing: for recurrent and refractory disease, and for non albicans species.
- Nucleic acid amplification panels: detect Candida species together with bacterial vaginosis organisms and Trichomonas vaginalis, and are used where available.
- Additional testing: diabetes screen and HIV test for recurrent disease.
Uncomplicated disease
| Agent | Regimen |
|---|---|
| Fluconazole | 150 mg orally, single dose |
| Clotrimazole 1 percent cream | 5 g intravaginally daily for 7 to 14 days |
| Clotrimazole 2 percent cream | 5 g intravaginally daily for 3 days |
| Clotrimazole vaginal tablet | 100 mg daily for 7 days, or 500 mg single dose |
| Miconazole 2 percent cream | 5 g intravaginally daily for 7 days |
| Miconazole vaginal suppository | 200 mg daily for 3 days, or 1200 mg single dose |
| Terconazole | 0.4 percent cream 5 g daily for 7 days, or 0.8 percent cream 5 g daily for 3 days, or 80 mg suppository daily for 3 days |
| Butoconazole 2 percent cream | 5 g intravaginally, single dose |
| Nystatin vaginal tablet | 100 000 units daily for 14 days |
Cure rates are similar with oral and topical azoles, at 80 to 90 percent. Patients choose by preference and cost. Oil based creams and suppositories weaken latex condoms and diaphragms. Itch is relieved by cool compresses, and topical corticosteroid is avoided except for a short period in severe vulvar inflammation, because it can delay cure.
Severe or complicated disease
- Fluconazole 150 mg orally, repeated after 72 hours (two doses), or a topical azole for 7 to 14 days.
- Diabetes is optimised, and the dose and duration are extended in immunosuppressed women.
Recurrent vulvovaginal candidiasis
Recurrence follows persisting host susceptibility and not drug resistance in most women. Culture confirms the diagnosis and the species before long term therapy.
- Induction: fluconazole 100, 150 or 200 mg orally every 72 hours for three doses, or a topical azole for 10 to 14 days.
- Maintenance: fluconazole 100 to 150 mg orally once weekly for 6 months.
Recurrence follows in about 30 to 50 percent after maintenance stops. Topical maintenance with clotrimazole 500 mg vaginal tablet weekly is an alternative where oral azoles are unsuitable. Ibrexafungerp 300 mg orally twice daily for one day and oteseconazole are newer options.
- Oteseconazole: 600 mg on day 1, 450 mg on day 2, then 150 mg weekly from day 14 for 11 weeks. It is used only in women not of reproductive potential, because it persists for months and is contraindicated in women who may become pregnant and in lactation.
- Ibrexafungerp: contraindicated in pregnancy. It is a triterpenoid glucan synthase inhibitor with activity against azole resistant Candida.
Non albicans disease
| Species | Treatment |
|---|---|
| Candida glabrata (azole susceptible dose dependent or resistant) | Boric acid 600 mg in a gelatin capsule intravaginally nightly for 14 days (first line); nystatin vaginal suppository 100 000 units daily for 14 days; flucytosine 17 percent cream 5 g nightly for 14 days (compounded) |
| Candida krusei | Topical azole for 7 to 14 days, because fluconazole is inactive; boric acid as an alternative |
| Candida parapsilosis, Candida tropicalis | Fluconazole or a topical azole, with longer courses in recurrent disease |
Boric acid is toxic by mouth, is used only intravaginally, and is avoided in pregnancy. It can cause local irritation and burning.
Special situations
- Pregnancy: topical azoles (clotrimazole, miconazole) for 7 days. Oral fluconazole is avoided because high dose exposure in the first trimester causes congenital anomalies, and observational data link even low dose exposure to miscarriage.
- Diabetes: glycaemic control, and review of SGLT2 inhibitor use in recurrent disease.
- HIV: treatment as in immunocompetent women, with antiretroviral therapy.
- Partners: routine treatment is not needed. Symptomatic male partners are treated topically.
- Control of triggers: avoid vaginal douching, perfumed products and unnecessary antibacterials, and use cotton underwear.
Drug safety
Fluconazole interacts with warfarin, phenytoin, sulphonylureas and QT prolonging drugs, and the dose is halved when creatinine clearance is below 50 mL per minute. Weekly maintenance for 6 months needs attention to liver tests in patients with other hepatotoxic exposure.
