












Organophosphate Poisoning
Also known as: Pesticide poisoning, Cholinergic toxidrome
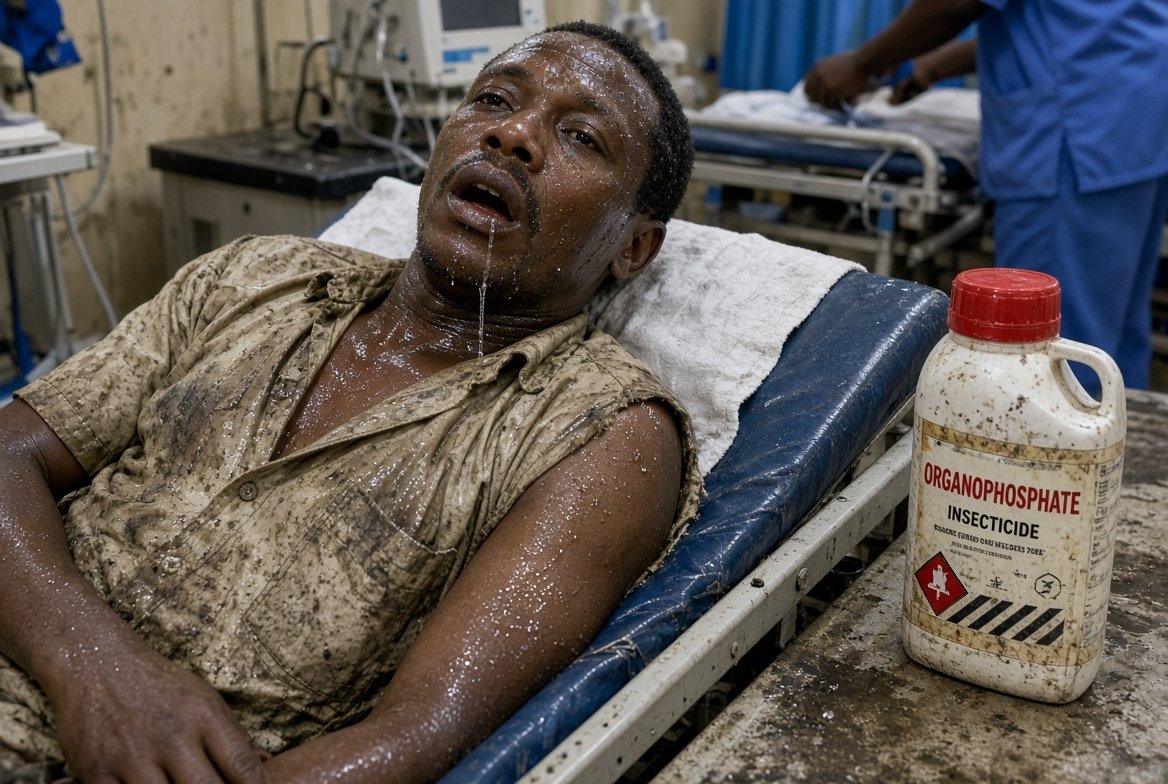
Organophosphates are a class of compounds, most commonly encountered as agricultural pesticides (and, historically and in some conflict settings, as nerve agents), that cause toxicity through irreversible inhibition of acetylcholinesterase.
This leads to accumulation of acetylcholine at both muscarinic and nicotinic synapses throughout the body, producing a characteristic and predictable toxidrome.
Exposure may occur through ingestion (the most common route in deliberate self harm, particularly significant in agricultural communities with ready pesticide access), dermal absorption, or inhalation.
The cholinergic toxidrome is classically remembered through the mnemonics SLUDGE (Salivation, Lacrimation, Urination, Defecation, Gastrointestinal upset, Emesis) for muscarinic effects, and DUMBELS as an alternative that adds Bradycardia, Bronchorrhea, and Bronchospasm, both pointing toward the same underlying muscarinic excess.
- Muscarinic effects: bradycardia, hypotension, excessive salivation, bronchorrhea and bronchospasm (a major cause of death, from a combination of secretions and airway constriction), miosis, sweating, vomiting, diarrhea, and urinary incontinence.
- Nicotinic effects: muscle fasciculation, weakness progressing to paralysis (including respiratory muscle weakness, a critical driver of mortality), tachycardia, and hypertension, the latter two sometimes masking or offsetting the muscarinic bradycardia and hypotension.
- Central nervous system effects: confusion, agitation, seizures, and coma in severe poisoning.
An intermediate syndrome can follow the acute cholinergic crisis, typically 24 to 96 hours after exposure, characterized by proximal muscle weakness and respiratory muscle involvement, and represents a distinct, delayed phase of risk requiring ongoing vigilance even after the initial cholinergic features have settled.
Diagnosis is primarily clinical, based on a compatible exposure history and the characteristic toxidrome.
- Red blood cell (or plasma) cholinesterase activity supports diagnosis and can be used to gauge severity and monitor recovery, though results are often not available urgently enough to guide immediate treatment decisions.
- ECG should be checked, given the risk of bradyarrhythmia and QT prolongation.
- ABG and electrolytes assess for respiratory failure and metabolic derangement.
Differentials include other toxidromes (particularly opioid toxicity, which shares miosis but lacks the excessive secretions and fasciculations), other causes of a seizure or reduced consciousness, and other pesticide or nerve agent exposures.
Personal protective equipment for staff is essential before approaching a contaminated patient, given the real risk of secondary exposure to healthcare workers from a patient's clothing, skin, or vomitus.
- Decontamination: remove all contaminated clothing and thoroughly wash the skin, since ongoing dermal absorption can perpetuate toxicity.
- Airway and breathing are the immediate priority given the risk of respiratory failure from bronchorrhea, bronchospasm, and respiratory muscle weakness; early intubation should be considered proactively rather than reactively in significant poisoning.
- Atropine is the mainstay antidote for the muscarinic effects. Give 1 to 2 mg intravenously in adults (0.02 mg/kg in children, minimum 0.1 mg, maximum 0.5 mg per dose) as an initial bolus, doubling the dose every 5 minutes if the response is inadequate, titrated against bronchial secretions and heart rate rather than pupil size, until secretions dry up. Cumulative doses commonly reach 10 to 20 mg in the first 2 to 3 hours and occasionally up to 50 mg in the first 24 hours in severe poisoning; tachycardia is an expected effect of adequate atropinisation and is not a reason to withhold further doses.
- Pralidoxime (or another oxime, availability varies by setting) is given alongside atropine: 1 to 2 g intravenously over 15 to 30 minutes as a loading dose in adults (25 to 50 mg/kg in children), followed by a continuous infusion of 400 to 600 mg/hour in adults (10 to 20 mg/kg/hour in children), or repeated bolus doses if an infusion is not practical. It works by reactivating acetylcholinesterase if given before the enzyme phosphate bond irreversibly "ages," and is most effective when started early; it addresses the nicotinic effects (including muscle weakness) that atropine does not treat.
- Benzodiazepines are used for seizures.
- Supportive care in an ICU setting is required for significant poisoning, given the risk of prolonged ventilatory support needs from both the acute cholinergic crisis and any subsequent intermediate syndrome.
Referral: poison control or toxicology service for all significant exposures; ICU for any respiratory compromise, significant cholinergic crisis, or need for ongoing atropine titration.
