












Renal Tubular Acidosis
Also known as: RTA
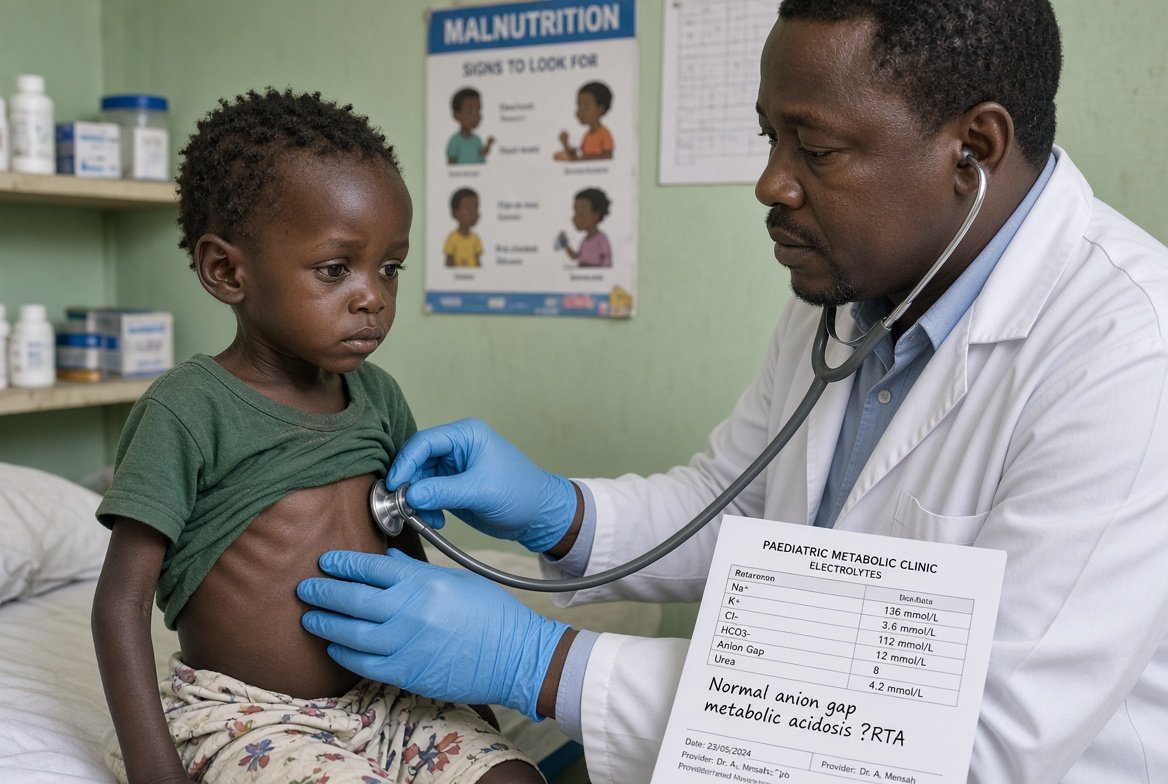
Renal tubular acidosis is a normal anion gap (hyperchloraemic) metabolic acidosis caused by defective renal acid handling, with a preserved or only mildly reduced glomerular filtration rate.
Three types are clinically relevant, and they differ in mechanism, potassium, urine pH and complications:
Type 1 (distal): failure of hydrogen ion secretion in the distal tubule. Hypokalaemia, urine pH persistently above 5.5, and a high risk of nephrocalcinosis and calcium phosphate stones. Causes include Sjögren's syndrome, other autoimmune disease, amphotericin, lithium, and hereditary forms
Type 2 (proximal): failure of bicarbonate reabsorption in the proximal tubule. Hypokalaemia, urine pH variable (below 5.5 once serum bicarbonate falls below the reabsorptive threshold), often part of Fanconi syndrome with glycosuria, aminoaciduria, phosphaturia and uricosuria. Causes include myeloma, tenofovir, acetazolamide, heavy metals and hereditary forms
Type 4 (hyperkalaemic): hypoaldosteronism or aldosterone resistance. Hyperkalaemia, urine pH usually below 5.5, and mild acidosis. This is the commonest type in adults, and is typically seen in diabetes, chronic kidney disease, and with ACE inhibitors, ARBs, spironolactone, trimethoprim, NSAIDs and heparin
Type 3 is a rare combined form and is not used in routine practice.
